







Bhupinder (Boo) Dhaliwale
bonviva/Ibandronic Acid Tabs
Bonviva is used for the treatment of osteoporosis (a disease that weakens bones) in postmenopausal women at risk of bone fractures. Studies have shown that it reduces the risk of spinal fractures, but its effectiveness in femoral (hip) neck fractures has not been guaranteed. This medication can only be dispensed with a prescription.

Consult

Select

Checkout
01
Select
the items you wish
to order
02
Order reviewed
by our qualified
prescriber
03
Delivered
to your door step
Your Selection
Please use the options provided to make your final selection.
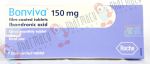
bonviva/Ibandronic Acid Tabs
£63
Total

You’re almost there!
It is the prescribers duty to ensure that the medicine is being used safely and appropriately. please answer a few questions about yourself to help us process your request.
- Manesha
Customer Service Team
Confidentiality & Authenticity Assured
- Fully Regulated UK Pharmacy
- Authentic UK sourced medicines only.
- Trading for more than 10 years.
- Information Governance lead ensures all data is confidential
Need Help With Your Questionnaire?
Our customer service team is on hand Monday-Friday to help you with your queries.
Please call us on 08009788956 or
email us at: headoffice@pharmacyplanet.com
Price Comparison
Select your preferred options and see the best price
| Pack | Price (£) | ||
|---|---|---|---|
| Ibandronic Acid (generic) | 150mg | 1 Tablet | 29.00 |
| Ibandronic Acid (generic) | 150mg | 2 Tablets | 45.00 |
| Ibandronic Acid (generic) | 150mg | 3 tablets | 56.00 |
| Bonviva | 150mg | 1 Tablet | 63.00 |
| Bonviva | 150mg | 2 Tablets | 120.00 |
| Bonviva | 150mg | 3 tablets | 159.00 |
It looks like you missed filling in questions from the last consultation.Click Here to submit your response.

No subscriptions or hidden fees

Secure checkout

UK Regulated online pharmacy

Trusted by over 250,000+ happy customers
One Day a Month: A Different Approach to Treating Osteoporosis
Long-term treatment for a chronic condition asks something significant of a patient. It asks for consistency, year after year, without the reinforcement of visible symptoms or immediate relief that shorter-term medicines provide. How a medicine fits into real life matters – and dosing frequency is one of the most practical dimensions of that fit. Bonviva/Ibandronic Acid Tabs 150mg are taken once every calendar month, on the same date each month, making them the only oral bisphosphonate in the Pharmacy Planet osteoporosis catalogue prescribed on a monthly rather than a daily or weekly schedule.
Twelve doses a year. One morning each month on which the pre-dose fasting and posture requirements apply. For patients who find a daily or weekly routine difficult to maintain, the monthly schedule represents a meaningful difference in the practicalities of long-term bone protection. Ibandronic acid 150mg is licensed in the UK for the treatment of osteoporosis in postmenopausal women to reduce the risk of vertebral fractures. It is a Prescription Only Medicine. A clinical consultation with a registered prescriber is required before any supply can take place.
Bonviva and Ibandronic Acid: Understanding What This Medicine Is
Bonviva is the branded originator tablet containing ibandronic acid at a dose of 150mg. Generic ibandronic acid 150mg tablets are therapeutically interchangeable alternatives, bioequivalent to the branded product and subject to the same UK regulatory approval requirements. For the purposes of this page, both are referred to as ibandronic acid 150mg.
Ibandronic acid is a nitrogen-containing bisphosphonate. It shares its core pharmacological class with alendronate and risedronate – medicines that are also represented in this catalogue – but ibandronic acid has a distinct molecular structure and a significantly higher binding affinity for bone mineral than either of those medicines. This higher affinity means that a larger single dose can be administered less frequently while maintaining a sustained pharmacological effect on bone resorption between doses.
The 150mg once-monthly tablet is the oral formulation of ibandronate approved for postmenopausal osteoporosis in the UK. Ibandronate is also available as a three-monthly intravenous injection (Bonviva injection), but that formulation is administered in clinical settings and is a separate product not covered here. The 150mg oral tablet is the formulation relevant to patients seeking oral, home-administered treatment.
It is important to note that the once-monthly 150mg tablet is licensed specifically for the treatment of osteoporosis in postmenopausal women to reduce vertebral fracture risk. It is not currently licensed for the treatment of osteoporosis in men at this dose and route, nor for glucocorticoid-induced bone loss – indications that are covered by other bisphosphonates in the catalogue. The prescriber will confirm which formulation is appropriate based on the patient's diagnosis and clinical circumstances.
Inside the Bone: The Science Behind Monthly Dosing
Bone is not an inert scaffold. It is a living system that responds to hormonal signals, mechanical load, and nutritional input – and it remodels continuously throughout adult life. After the menopause, the loss of oestrogen removes a key hormonal brake on osteoclast activity. Osteoclasts – the cells responsible for dissolving old bone – become more numerous and more active. Osteoblasts, which build new bone, cannot keep pace. The cumulative effect, over months and years, is a progressive reduction in both bone mineral density and the quality of internal bone architecture.
Ibandronic acid targets this imbalance at the osteoclast level. After absorption, it binds with high affinity to hydroxyapatite crystals on bone surfaces, concentrating at sites of active resorption. When osteoclasts attempt to resorb bone at those sites, they internalise the ibandronate. Within the osteoclast, ibandronate inhibits farnesyl pyrophosphate synthase – the same mevalonate pathway enzyme targeted by alendronate and risedronate – disrupting the production of isoprenoid lipids that are essential to osteoclast structural integrity.
What distinguishes ibandronate's pharmacology is the duration of its effect relative to the dose interval. Its significantly higher binding affinity for bone mineral – greater than that of alendronate or risedronate – means that a single 150mg dose can sustain a clinically meaningful suppression of bone resorption across the entire following month. Biochemical markers of bone resorption remain suppressed throughout the inter-dose interval, supporting the pharmacological rationale for once-monthly rather than once-weekly administration.
Clinical evidence from trials including MOBILE (Monthly Oral iBandronate In LadiEs) demonstrated that the 150mg once-monthly tablet produced bone mineral density gains at the lumbar spine and hip comparable to the daily ibandronate regimen it replaced, supporting the transition to monthly oral dosing as a clinically valid and effective treatment schedule.
Your Monthly Dose: Timing, Technique, and What Not to Miss
Choose a date within the first few days of each calendar month and take your 150mg ibandronic acid tablet on that same date every month. Write the date down. Set a recurring reminder on your phone or calendar. Because the dose interval is twenty-eight to thirty-one days, it is easy to miscalculate the next date if you rely on memory alone. Choosing a fixed calendar date – the first, the fifth, the tenth of every month – is simpler and more reliable than counting days.
Take the tablet on your chosen morning before any food, any drink other than plain tap water, or any other oral medicine. The pre-dose fasting requirement exists because ibandronate, like all oral bisphosphonates, is poorly absorbed when food, mineral drinks, or other medicines are present in the stomach at the time of dosing. Only plain tap water should be used to swallow the tablet. Use a full glass – at least 180ml.
Swallow the tablet whole. Do not crush, chew, or split it. Sit or stand upright – do not lie down – for at least sixty minutes after taking the tablet. This sixty-minute upright window is longer than the thirty-minute window required for alendronate and risedronate, and it is specific to the 150mg once-monthly ibandronate dose. It reflects the larger tablet mass and the importance of ensuring complete transit through the oesophagus before the patient resumes normal activity.
After the sixty-minute window has passed, you may eat breakfast, drink normally, and take any other medicines or supplements. Calcium supplements, antacids, and any preparation containing iron or magnesium should be taken at a separate time from the ibandronate dose – at least sixty minutes after taking the tablet.
If you forget your monthly dose and remember within seven days of your chosen date, take it as soon as you remember and then resume your usual monthly date the following month. If more than seven days have passed since your chosen date, skip the missed dose entirely and take your next tablet on your usual date the following month. Do not take two tablets within the same month under any circumstances. Contact your pharmacist if you are unsure what to do.
One Tablet, Once a Month: Understanding the Dose
The Licensed Oral Formulation
Ibandronic acid for oral use in postmenopausal osteoporosis is available as a single licensed oral dose of 150mg taken once every calendar month. There is no dosing titration with this formulation; every patient receives the same 150mg dose.
| Product | Strength | Frequency | Upright Period After Dose | Fasting Before |
|---|---|---|---|---|
| Bonviva / Ibandronic Acid | 150mg | Once monthly | At least 60 minutes | Before first food or drink |
Why Sixty Minutes – Not Thirty?
Patients already familiar with alendronate or risedronate will notice that the upright window for ibandronate is sixty minutes, compared to the thirty minutes specified for those medicines. This longer window reflects the higher tablet mass of the 150mg dose and the prescribing guidance in the current UK SmPC. The sixty-minute requirement should be observed precisely and is not interchangeable with the shorter window used for other bisphosphonates. Patients who are switching to ibandronate from another bisphosphonate should be aware of this difference from their first dose.
Frequency and Annual Dose Burden
Twelve tablets per year. This is the total annual tablet burden for a patient on ibandronic acid 150mg once monthly. By comparison, a patient on once-weekly alendronate takes fifty-two tablets per year; a patient on daily sodium clodronate takes between two hundred and ninety and five hundred and eighty-five tablets per year depending on dose. For patients who value simplicity in their long-term regimen, this reduction in total tablet burden is a clinically meaningful feature of the monthly schedule.
Prescribing note: the once-monthly 150mg oral tablet is licensed specifically for postmenopausal osteoporosis. It is not licensed for men or for glucocorticoid-induced bone loss at this dose. Patients being prescribed ibandronate for the first time should ensure their diagnosis and indication are clearly communicated during their consultation.
Supplementation Guidance
As with all oral bisphosphonate therapy, prescribers frequently advise patients to take calcium and vitamin D alongside ibandronate to support bone mineralisation. These supplements must be taken at least sixty minutes after the monthly ibandronate dose, never at the same time. Your prescriber will advise whether supplementation is appropriate for your individual nutritional circumstances.
Take ibandronic acid exactly as your prescriber has directed. Do not alter the dose, frequency, or date without first speaking to your prescriber or pharmacist.
What Your Body Might Tell You: Side Effects and When to Act
Ibandronic acid is generally well tolerated. The once-monthly dosing schedule means that any gastrointestinal effects, if they occur, arise on one morning each month rather than weekly or daily – a pattern that, for some patients, makes individual episodes more manageable than those occurring with more frequent dosing schedules. The following information reflects the current UK SmPC for ibandronic acid 150mg.
Common Side Effects (may affect up to 1 in 10 people)
- Oesophagitis, dysphagia (difficulty swallowing), or pain on swallowing
- Abdominal pain, discomfort, or bloating
- Nausea or feeling sick
- Indigestion or acid reflux
- Diarrhoea or constipation
- Musculoskeletal pain, including bone, joint, or muscle ache
- Headache
Uncommon Side Effects (may affect up to 1 in 100 people)
- Gastric or duodenal ulceration
- Gastritis
- Skin rash or pruritus
- Acute phase reaction after the first dose: fever, muscle aches, and flu-like symptoms. These typically resolve within a few days and are less likely to recur with subsequent monthly doses.
- Low blood calcium (hypocalcaemia), particularly in patients with vitamin D deficiency
- Eye inflammation, including uveitis or episcleritis
Rare but Serious Adverse Effects
The following serious adverse effects are associated with bisphosphonate therapy, including ibandronate. They are uncommon but require awareness throughout the course of treatment.
- Osteonecrosis of the jaw (ONJ): rare deterioration of jaw bone, predominantly associated with invasive dental procedures. Patients must inform their dentist that they are taking ibandronate before any planned tooth extraction, implant procedure, or oral surgery. Good dental hygiene and regular check-ups are recommended.
- Atypical femoral fractures: unusual stress fractures at non-classic sites of the thigh bone, associated with prolonged bisphosphonate use. Patients who develop gradually worsening thigh, hip, or groin pain should inform their prescriber promptly, without waiting for a scheduled review. Bilateral pain should also be investigated.
- Severe or incapacitating musculoskeletal pain, which may resolve on stopping the medicine – but treatment should not be stopped without medical advice
- Severe cutaneous reactions, including Stevens-Johnson syndrome (very rare)
Report any side effects directly to the MHRA via the Yellow Card scheme at yellowcard.mhra.gov.uk, or through your prescriber or pharmacist.
Is Ibandronic Acid Right for You? Suitability and Contraindications
The Licensed Patient Group
Ibandronic acid 150mg once-monthly tablets are licensed specifically for the treatment of osteoporosis in postmenopausal women to reduce the risk of vertebral fractures. This is a defined and specific licensed indication. It does not currently extend to men, to premenopausal women, or to osteoporosis caused by glucocorticoid therapy. Patients should be clear that their diagnosis falls within the licensed indication before proceeding with a consultation.
Within the postmenopausal osteoporosis indication, suitability is assessed individually. The prescriber will consider bone density measurements, fracture history, concurrent medicines, relevant comorbidities, and any previous experience with bisphosphonate therapy before making a prescribing decision.
When Ibandronate Is Not Appropriate
Ibandronic acid 150mg is not suitable for patients with any of the following.
- Uncorrected hypocalcaemia at the time of commencing treatment – this must be corrected before any bisphosphonate is started
- Severe renal impairment, defined as creatinine clearance below 30ml per minute – ibandronate is contraindicated at this level of renal function
- Known hypersensitivity to ibandronic acid or any excipient in the tablet formulation
- Inability to stand or sit upright for at least sixty minutes after taking the dose
- Oesophageal conditions that impair normal oesophageal emptying, such as stricture or achalasia – these conditions significantly increase the risk of oesophageal adverse effects
Active upper gastrointestinal conditions – including oesophagitis, Barrett's oesophagus, or active gastric ulceration – should be disclosed to the prescriber before initiating treatment. These may represent contraindications or require clinical evaluation.
Ibandronate is not licensed for use in children or adolescents, and it is not recommended during pregnancy or breastfeeding. Women with mild to moderate renal impairment can use ibandronate, but the prescriber will assess renal function as part of the consultation. Patients with renal impairment approaching the threshold for contraindication should inform their prescriber of any concurrent medicines that may affect kidney function.
Starting Your Journey: The Consultation Process at Pharmacy Planet
Ibandronic acid 150mg is a Prescription Only Medicine. A clinical consultation is the essential and primary step before any supply can take place. The consultation is not a formality – it is the mechanism by which a registered prescriber determines, on the basis of your individual clinical circumstances, whether this medicine is appropriate for you. A prescription is a possible outcome of the consultation, not something that is guaranteed at the outset.
The Pharmacy Planet online consultation will ask you to provide information about your postmenopausal status, your bone health history including any previous DEXA scan results or fracture risk assessments, any previous bisphosphonate treatment, your renal function history, and all medicines you are currently taking. This information directly informs the prescriber's clinical decision.
Patients who have been taking ibandronate or another bisphosphonate and are seeking ongoing supply through Pharmacy Planet will also need to complete a consultation. The prescriber will confirm that continued treatment remains clinically appropriate and that no new circumstances – for example, a change in renal function, a new diagnosis, or a new medicine – have arisen that would warrant clinical review before continuing.
If the prescriber needs additional clinical information before making a prescribing decision, you will be clearly informed and guided on how to provide it. Our pharmacy team is available to assist with questions about the consultation process, the administration of the medicine, or any aspect of your ongoing treatment.
Looking After Your Monthly Tablet: Storage and Safe Disposal
Store ibandronic acid 150mg tablets below 30 degrees Celsius. Keep them in their original blister packaging, away from direct light and moisture. Once-monthly dosing means that a single blister strip or pack covers several months of treatment – taking care of the packaging over an extended period is therefore more relevant here than for daily or weekly medicines.
Because you take only one tablet per month, it is especially important to track your dose carefully. Mark your monthly dosing date on a calendar, in a diary, or on your phone immediately after taking each tablet. This prevents both missed doses and accidental double doses – the latter of which must be avoided.
Check the expiry date printed on the blister before each monthly dose. The date refers to the last day of the stated month. Do not use tablets beyond their expiry date. Return any unused, expired, or unwanted tablets to a pharmacy for safe and environmentally responsible disposal. Medicines must not be placed in household bins or flushed into drains.
Comparing Oral Osteoporosis Treatments: What You Need to Know
All seven medicines listed below are oral tablets or capsules prescribed for osteoporosis, the same therapeutic category and the same form factor, making direct comparison appropriate. They differ in their active ingredient, dosing frequency, licensed indication, and mechanism of action.
The table below compares commonly prescribed oral bisphosphonate treatments available through Pharmacy Planet's osteoporosis service. Products are listed in order of dosing frequency, from daily to monthly, so you can quickly identify how each medicine fits into a patient's routine.
| Product | Form | How Often Taken | Dose | Main Licensed Use | Effect Timeline | Key Patient Note |
|---|---|---|---|---|---|---|
| Alendronic Acid SF Oral Solution | Oral liquid (sugar-free) | Once daily | 70mg / 100ml | Osteoporosis in postmenopausal women and men | Bone density change measurable from 6 months | Sugar-free liquid for patients unable to swallow tablets. Suitable for diabetics. Take with plain water; remain upright 30 min after dose. |
| Alendronic Acid / Fosamax Daily | Film-coated tablet | Once daily | 10mg | Osteoporosis in postmenopausal women and men | Bone density change measurable from 6 months | Original daily alendronate. Same total weekly dose as the 70mg weekly tablet. Daily GI exposure – some patients tolerate weekly schedule better. Upright 30 min after. |
| Actonel / Risedronate Daily | Film-coated tablet | Once daily | 5mg | Osteoporosis in postmenopausal women; men; and glucocorticoid-induced osteoporosis | Bone density change measurable from 6 months | Only product in this catalogue with a specific licence for glucocorticoid (steroid)-induced bone loss. Upright 30 min after dose. |
| Bonefos / Sodium Clodronate | Capsule (400mg) or Tablet (800mg) | Once daily | 800mg–1600mg daily | Osteoporosis; also osteolysis and hypercalcaemia in malignant disease | Bone turnover marker reduction from weeks; density change from months | Only non-nitrogen bisphosphonate here – different cellular mechanism to all others. Food-free window required 2 hrs BEFORE and AFTER dose. Requires renal monitoring. Avoid concurrent NSAIDs. |
| Actonel / Risedronate Once Weekly | Film-coated tablet | Once weekly | 35mg | Osteoporosis in postmenopausal women to reduce vertebral fracture risk | Bone density change measurable from 6 months | Licensed specifically for postmenopausal women at this dose – not men. One dose per week on a fixed chosen day. Upright 30 min after dose. |
Important: This comparison is for general information only and does not replace medical advice. A prescriber will decide which treatment is suitable for you following an online consultation. All medicines listed are Prescription Only Medicines (POMs). Suitability depends on individual clinical circumstances including diagnosis, renal function, medical history, and concurrent medicines.
Pharmacy Planet: Where Regulated Care Meets Real Convenience
Pharmacy Planet is a GPhC-registered online pharmacy providing prescription medicine services to patients across the UK. Every prescription we dispense is reviewed by a qualified pharmacist before dispatch, and our entire clinical and operational framework is built around the safety of the patients we serve.
For patients managing long-term osteoporosis treatment, having a reliable, regulated, and accessible pharmacy service matters. Once-monthly medicines in particular require careful ongoing management of supply timing – receiving your prescription at the right point each month, without gaps. Our repeat consultation and dispensing service is designed to support exactly that kind of consistent access.
We are committed to transparent, honest, clinically grounded communication with every patient who uses our service. Our pharmacist team is available to answer questions about your ibandronate treatment, to clarify any aspect of the administration guidance, and to raise clinical concerns with the prescribing team where needed. Access to safe care, delivered with respect and clarity, is what we are here to provide.
References
- electronic Medicines Compendium (emc). Bonviva 150mg Film-Coated Tablets / Ibandronic Acid 150mg Tablets – Summary of Product Characteristics. www.medicines.org.uk/emc. Accessed June 2026.
- British National Formulary (BNF). Ibandronic acid. bnf.nice.org.uk/drugs/ibandronic-acid. Accessed June 2026.
- NHS. Ibandronic acid. www.nhs.uk/medicines/ibandronic-acid. Accessed June 2026.
- National Osteoporosis Guideline Group (NOGG). Clinical Guideline for the Prevention and Treatment of Osteoporosis. www.nogg.org.uk. Accessed June 2026.
- Miller PD, et al. Monthly oral ibandronate therapy in postmenopausal osteoporosis: 1-year results from the MOBILE study. Journal of Bone and Mineral Research. 2005;20(8):1315-1322.
Bonviva/Ibandronic Acid
Long-term treatment for a chronic condition asks something significant of a patient. It asks for consistency, year after year, without the reinforcement of visible symptoms or immediate relief that shorter-term medicines provide. How a medicine fits into real life matters – and dosing frequency is one of the most practical dimensions of that fit. Bonviva/Ibandronic Acid Tabs 150mg are taken once every calendar month, on the same date each month, making them the only oral bisphosphonate in the Pharmacy Planet osteoporosis catalogue prescribed on a monthly rather than a daily or weekly schedule.
Twelve doses a year. One morning each month on which the pre-dose fasting and posture requirements apply. For patients who find a daily or weekly routine difficult to maintain, the monthly schedule represents a meaningful difference in the practicalities of long-term bone protection. Ibandronic acid 150mg is licensed in the UK for the treatment of osteoporosis in postmenopausal women to reduce the risk of vertebral fractures. It is a Prescription Only Medicine. A clinical consultation with a registered prescriber is required before any supply can take place.
Bonviva is the branded originator tablet containing ibandronic acid at a dose of 150mg. Generic ibandronic acid 150mg tablets are therapeutically interchangeable alternatives, bioequivalent to the branded product and subject to the same UK regulatory approval requirements. For the purposes of this page, both are referred to as ibandronic acid 150mg.
Ibandronic acid is a nitrogen-containing bisphosphonate. It shares its core pharmacological class with alendronate and risedronate – medicines that are also represented in this catalogue – but ibandronic acid has a distinct molecular structure and a significantly higher binding affinity for bone mineral than either of those medicines. This higher affinity means that a larger single dose can be administered less frequently while maintaining a sustained pharmacological effect on bone resorption between doses.
The 150mg once-monthly tablet is the oral formulation of ibandronate approved for postmenopausal osteoporosis in the UK. Ibandronate is also available as a three-monthly intravenous injection (Bonviva injection), but that formulation is administered in clinical settings and is a separate product not covered here. The 150mg oral tablet is the formulation relevant to patients seeking oral, home-administered treatment.
It is important to note that the once-monthly 150mg tablet is licensed specifically for the treatment of osteoporosis in postmenopausal women to reduce vertebral fracture risk. It is not currently licensed for the treatment of osteoporosis in men at this dose and route, nor for glucocorticoid-induced bone loss – indications that are covered by other bisphosphonates in the catalogue. The prescriber will confirm which formulation is appropriate based on the patient's diagnosis and clinical circumstances.
Bone is not an inert scaffold. It is a living system that responds to hormonal signals, mechanical load, and nutritional input – and it remodels continuously throughout adult life. After the menopause, the loss of oestrogen removes a key hormonal brake on osteoclast activity. Osteoclasts – the cells responsible for dissolving old bone – become more numerous and more active. Osteoblasts, which build new bone, cannot keep pace. The cumulative effect, over months and years, is a progressive reduction in both bone mineral density and the quality of internal bone architecture.
Ibandronic acid targets this imbalance at the osteoclast level. After absorption, it binds with high affinity to hydroxyapatite crystals on bone surfaces, concentrating at sites of active resorption. When osteoclasts attempt to resorb bone at those sites, they internalise the ibandronate. Within the osteoclast, ibandronate inhibits farnesyl pyrophosphate synthase – the same mevalonate pathway enzyme targeted by alendronate and risedronate – disrupting the production of isoprenoid lipids that are essential to osteoclast structural integrity.
What distinguishes ibandronate's pharmacology is the duration of its effect relative to the dose interval. Its significantly higher binding affinity for bone mineral – greater than that of alendronate or risedronate – means that a single 150mg dose can sustain a clinically meaningful suppression of bone resorption across the entire following month. Biochemical markers of bone resorption remain suppressed throughout the inter-dose interval, supporting the pharmacological rationale for once-monthly rather than once-weekly administration.
Clinical evidence from trials including MOBILE (Monthly Oral iBandronate In LadiEs) demonstrated that the 150mg once-monthly tablet produced bone mineral density gains at the lumbar spine and hip comparable to the daily ibandronate regimen it replaced, supporting the transition to monthly oral dosing as a clinically valid and effective treatment schedule.
Choose a date within the first few days of each calendar month and take your 150mg ibandronic acid tablet on that same date every month. Write the date down. Set a recurring reminder on your phone or calendar. Because the dose interval is twenty-eight to thirty-one days, it is easy to miscalculate the next date if you rely on memory alone. Choosing a fixed calendar date – the first, the fifth, the tenth of every month – is simpler and more reliable than counting days.
Take the tablet on your chosen morning before any food, any drink other than plain tap water, or any other oral medicine. The pre-dose fasting requirement exists because ibandronate, like all oral bisphosphonates, is poorly absorbed when food, mineral drinks, or other medicines are present in the stomach at the time of dosing. Only plain tap water should be used to swallow the tablet. Use a full glass – at least 180ml.
Swallow the tablet whole. Do not crush, chew, or split it. Sit or stand upright – do not lie down – for at least sixty minutes after taking the tablet. This sixty-minute upright window is longer than the thirty-minute window required for alendronate and risedronate, and it is specific to the 150mg once-monthly ibandronate dose. It reflects the larger tablet mass and the importance of ensuring complete transit through the oesophagus before the patient resumes normal activity.
After the sixty-minute window has passed, you may eat breakfast, drink normally, and take any other medicines or supplements. Calcium supplements, antacids, and any preparation containing iron or magnesium should be taken at a separate time from the ibandronate dose – at least sixty minutes after taking the tablet.
If you forget your monthly dose and remember within seven days of your chosen date, take it as soon as you remember and then resume your usual monthly date the following month. If more than seven days have passed since your chosen date, skip the missed dose entirely and take your next tablet on your usual date the following month. Do not take two tablets within the same month under any circumstances. Contact your pharmacist if you are unsure what to do.
The Licensed Oral Formulation
Ibandronic acid for oral use in postmenopausal osteoporosis is available as a single licensed oral dose of 150mg taken once every calendar month. There is no dosing titration with this formulation; every patient receives the same 150mg dose.
| Product | Strength | Frequency | Upright Period After Dose | Fasting Before |
|---|---|---|---|---|
| Bonviva / Ibandronic Acid | 150mg | Once monthly | At least 60 minutes | Before first food or drink |
Why Sixty Minutes – Not Thirty?
Patients already familiar with alendronate or risedronate will notice that the upright window for ibandronate is sixty minutes, compared to the thirty minutes specified for those medicines. This longer window reflects the higher tablet mass of the 150mg dose and the prescribing guidance in the current UK SmPC. The sixty-minute requirement should be observed precisely and is not interchangeable with the shorter window used for other bisphosphonates. Patients who are switching to ibandronate from another bisphosphonate should be aware of this difference from their first dose.
Frequency and Annual Dose Burden
Twelve tablets per year. This is the total annual tablet burden for a patient on ibandronic acid 150mg once monthly. By comparison, a patient on once-weekly alendronate takes fifty-two tablets per year; a patient on daily sodium clodronate takes between two hundred and ninety and five hundred and eighty-five tablets per year depending on dose. For patients who value simplicity in their long-term regimen, this reduction in total tablet burden is a clinically meaningful feature of the monthly schedule.
Prescribing note: the once-monthly 150mg oral tablet is licensed specifically for postmenopausal osteoporosis. It is not licensed for men or for glucocorticoid-induced bone loss at this dose. Patients being prescribed ibandronate for the first time should ensure their diagnosis and indication are clearly communicated during their consultation.
Supplementation Guidance
As with all oral bisphosphonate therapy, prescribers frequently advise patients to take calcium and vitamin D alongside ibandronate to support bone mineralisation. These supplements must be taken at least sixty minutes after the monthly ibandronate dose, never at the same time. Your prescriber will advise whether supplementation is appropriate for your individual nutritional circumstances.
Take ibandronic acid exactly as your prescriber has directed. Do not alter the dose, frequency, or date without first speaking to your prescriber or pharmacist.
Ibandronic acid is generally well tolerated. The once-monthly dosing schedule means that any gastrointestinal effects, if they occur, arise on one morning each month rather than weekly or daily – a pattern that, for some patients, makes individual episodes more manageable than those occurring with more frequent dosing schedules. The following information reflects the current UK SmPC for ibandronic acid 150mg.
Common Side Effects (may affect up to 1 in 10 people)
- Oesophagitis, dysphagia (difficulty swallowing), or pain on swallowing
- Abdominal pain, discomfort, or bloating
- Nausea or feeling sick
- Indigestion or acid reflux
- Diarrhoea or constipation
- Musculoskeletal pain, including bone, joint, or muscle ache
- Headache
Uncommon Side Effects (may affect up to 1 in 100 people)
- Gastric or duodenal ulceration
- Gastritis
- Skin rash or pruritus
- Acute phase reaction after the first dose: fever, muscle aches, and flu-like symptoms. These typically resolve within a few days and are less likely to recur with subsequent monthly doses.
- Low blood calcium (hypocalcaemia), particularly in patients with vitamin D deficiency
- Eye inflammation, including uveitis or episcleritis
Rare but Serious Adverse Effects
The following serious adverse effects are associated with bisphosphonate therapy, including ibandronate. They are uncommon but require awareness throughout the course of treatment.
- Osteonecrosis of the jaw (ONJ): rare deterioration of jaw bone, predominantly associated with invasive dental procedures. Patients must inform their dentist that they are taking ibandronate before any planned tooth extraction, implant procedure, or oral surgery. Good dental hygiene and regular check-ups are recommended.
- Atypical femoral fractures: unusual stress fractures at non-classic sites of the thigh bone, associated with prolonged bisphosphonate use. Patients who develop gradually worsening thigh, hip, or groin pain should inform their prescriber promptly, without waiting for a scheduled review. Bilateral pain should also be investigated.
- Severe or incapacitating musculoskeletal pain, which may resolve on stopping the medicine – but treatment should not be stopped without medical advice
- Severe cutaneous reactions, including Stevens-Johnson syndrome (very rare)
Report any side effects directly to the MHRA via the Yellow Card scheme at yellowcard.mhra.gov.uk, or through your prescriber or pharmacist.
The Licensed Patient Group
Ibandronic acid 150mg once-monthly tablets are licensed specifically for the treatment of osteoporosis in postmenopausal women to reduce the risk of vertebral fractures. This is a defined and specific licensed indication. It does not currently extend to men, to premenopausal women, or to osteoporosis caused by glucocorticoid therapy. Patients should be clear that their diagnosis falls within the licensed indication before proceeding with a consultation.
Within the postmenopausal osteoporosis indication, suitability is assessed individually. The prescriber will consider bone density measurements, fracture history, concurrent medicines, relevant comorbidities, and any previous experience with bisphosphonate therapy before making a prescribing decision.
When Ibandronate Is Not Appropriate
Ibandronic acid 150mg is not suitable for patients with any of the following.
- Uncorrected hypocalcaemia at the time of commencing treatment – this must be corrected before any bisphosphonate is started
- Severe renal impairment, defined as creatinine clearance below 30ml per minute – ibandronate is contraindicated at this level of renal function
- Known hypersensitivity to ibandronic acid or any excipient in the tablet formulation
- Inability to stand or sit upright for at least sixty minutes after taking the dose
- Oesophageal conditions that impair normal oesophageal emptying, such as stricture or achalasia – these conditions significantly increase the risk of oesophageal adverse effects
Active upper gastrointestinal conditions – including oesophagitis, Barrett's oesophagus, or active gastric ulceration – should be disclosed to the prescriber before initiating treatment. These may represent contraindications or require clinical evaluation.
Ibandronate is not licensed for use in children or adolescents, and it is not recommended during pregnancy or breastfeeding. Women with mild to moderate renal impairment can use ibandronate, but the prescriber will assess renal function as part of the consultation. Patients with renal impairment approaching the threshold for contraindication should inform their prescriber of any concurrent medicines that may affect kidney function.
Ibandronic acid 150mg is a Prescription Only Medicine. A clinical consultation is the essential and primary step before any supply can take place. The consultation is not a formality – it is the mechanism by which a registered prescriber determines, on the basis of your individual clinical circumstances, whether this medicine is appropriate for you. A prescription is a possible outcome of the consultation, not something that is guaranteed at the outset.
The Pharmacy Planet online consultation will ask you to provide information about your postmenopausal status, your bone health history including any previous DEXA scan results or fracture risk assessments, any previous bisphosphonate treatment, your renal function history, and all medicines you are currently taking. This information directly informs the prescriber's clinical decision.
Patients who have been taking ibandronate or another bisphosphonate and are seeking ongoing supply through Pharmacy Planet will also need to complete a consultation. The prescriber will confirm that continued treatment remains clinically appropriate and that no new circumstances – for example, a change in renal function, a new diagnosis, or a new medicine – have arisen that would warrant clinical review before continuing.
If the prescriber needs additional clinical information before making a prescribing decision, you will be clearly informed and guided on how to provide it. Our pharmacy team is available to assist with questions about the consultation process, the administration of the medicine, or any aspect of your ongoing treatment.
Store ibandronic acid 150mg tablets below 30 degrees Celsius. Keep them in their original blister packaging, away from direct light and moisture. Once-monthly dosing means that a single blister strip or pack covers several months of treatment – taking care of the packaging over an extended period is therefore more relevant here than for daily or weekly medicines.
Because you take only one tablet per month, it is especially important to track your dose carefully. Mark your monthly dosing date on a calendar, in a diary, or on your phone immediately after taking each tablet. This prevents both missed doses and accidental double doses – the latter of which must be avoided.
Check the expiry date printed on the blister before each monthly dose. The date refers to the last day of the stated month. Do not use tablets beyond their expiry date. Return any unused, expired, or unwanted tablets to a pharmacy for safe and environmentally responsible disposal. Medicines must not be placed in household bins or flushed into drains.
All seven medicines listed below are oral tablets or capsules prescribed for osteoporosis, the same therapeutic category and the same form factor, making direct comparison appropriate. They differ in their active ingredient, dosing frequency, licensed indication, and mechanism of action.
The table below compares commonly prescribed oral bisphosphonate treatments available through Pharmacy Planet's osteoporosis service. Products are listed in order of dosing frequency, from daily to monthly, so you can quickly identify how each medicine fits into a patient's routine.
| Product | Form | How Often Taken | Dose | Main Licensed Use | Effect Timeline | Key Patient Note |
|---|---|---|---|---|---|---|
| Alendronic Acid SF Oral Solution | Oral liquid (sugar-free) | Once daily | 70mg / 100ml | Osteoporosis in postmenopausal women and men | Bone density change measurable from 6 months | Sugar-free liquid for patients unable to swallow tablets. Suitable for diabetics. Take with plain water; remain upright 30 min after dose. |
| Alendronic Acid / Fosamax Daily | Film-coated tablet | Once daily | 10mg | Osteoporosis in postmenopausal women and men | Bone density change measurable from 6 months | Original daily alendronate. Same total weekly dose as the 70mg weekly tablet. Daily GI exposure – some patients tolerate weekly schedule better. Upright 30 min after. |
| Actonel / Risedronate Daily | Film-coated tablet | Once daily | 5mg | Osteoporosis in postmenopausal women; men; and glucocorticoid-induced osteoporosis | Bone density change measurable from 6 months | Only product in this catalogue with a specific licence for glucocorticoid (steroid)-induced bone loss. Upright 30 min after dose. |
| Bonefos / Sodium Clodronate | Capsule (400mg) or Tablet (800mg) | Once daily | 800mg–1600mg daily | Osteoporosis; also osteolysis and hypercalcaemia in malignant disease | Bone turnover marker reduction from weeks; density change from months | Only non-nitrogen bisphosphonate here – different cellular mechanism to all others. Food-free window required 2 hrs BEFORE and AFTER dose. Requires renal monitoring. Avoid concurrent NSAIDs. |
| Actonel / Risedronate Once Weekly | Film-coated tablet | Once weekly | 35mg | Osteoporosis in postmenopausal women to reduce vertebral fracture risk | Bone density change measurable from 6 months | Licensed specifically for postmenopausal women at this dose – not men. One dose per week on a fixed chosen day. Upright 30 min after dose. |
Important: This comparison is for general information only and does not replace medical advice. A prescriber will decide which treatment is suitable for you following an online consultation. All medicines listed are Prescription Only Medicines (POMs). Suitability depends on individual clinical circumstances including diagnosis, renal function, medical history, and concurrent medicines.
Pharmacy Planet is a GPhC-registered online pharmacy providing prescription medicine services to patients across the UK. Every prescription we dispense is reviewed by a qualified pharmacist before dispatch, and our entire clinical and operational framework is built around the safety of the patients we serve.
For patients managing long-term osteoporosis treatment, having a reliable, regulated, and accessible pharmacy service matters. Once-monthly medicines in particular require careful ongoing management of supply timing – receiving your prescription at the right point each month, without gaps. Our repeat consultation and dispensing service is designed to support exactly that kind of consistent access.
We are committed to transparent, honest, clinically grounded communication with every patient who uses our service. Our pharmacist team is available to answer questions about your ibandronate treatment, to clarify any aspect of the administration guidance, and to raise clinical concerns with the prescribing team where needed. Access to safe care, delivered with respect and clarity, is what we are here to provide.
- electronic Medicines Compendium (emc). Bonviva 150mg Film-Coated Tablets / Ibandronic Acid 150mg Tablets – Summary of Product Characteristics. www.medicines.org.uk/emc. Accessed June 2026.
- British National Formulary (BNF). Ibandronic acid. bnf.nice.org.uk/drugs/ibandronic-acid. Accessed June 2026.
- NHS. Ibandronic acid. www.nhs.uk/medicines/ibandronic-acid. Accessed June 2026.
- National Osteoporosis Guideline Group (NOGG). Clinical Guideline for the Prevention and Treatment of Osteoporosis. www.nogg.org.uk. Accessed June 2026.
- Miller PD, et al. Monthly oral ibandronate therapy in postmenopausal osteoporosis: 1-year results from the MOBILE study. Journal of Bone and Mineral Research. 2005;20(8):1315-1322.
Frequently Asked Questions
Bonviva, containing ibandronic acid 150mg, is a prescription tablet taken once every calendar month for the treatment of osteoporosis in postmenopausal women. It is licensed specifically to reduce the risk of vertebral fractures – fractures occurring in the bones of the spine, which are common and often painful consequences of osteoporosis. It belongs to the nitrogen-containing bisphosphonate class and works by slowing osteoclast activity to reduce the rate at which bone is broken down. It is not currently licensed for men or for glucocorticoid-induced bone loss at this dose.
Ibandronate has a significantly higher binding affinity for bone mineral than alendronate or risedronate. This means that once a 150mg dose is incorporated into bone surfaces, it continues to suppress osteoclast activity for a full month between doses, without the effect wearing off. The pharmacological rationale for monthly dosing is therefore grounded in the medicine's behaviour within bone rather than a simple calculation of dose equivalence. Clinical data from the MOBILE study confirmed that the monthly 150mg tablet produces bone density responses comparable to daily ibandronate in postmenopausal women.
The sixty-minute upright requirement for ibandronate 150mg is specified in the UK SmPC for this formulation and reflects the higher dose mass relative to daily and weekly bisphosphonate tablets. Remaining upright ensures that the tablet passes efficiently through the oesophagus and into the stomach. Ibandronate, like all oral bisphosphonates, can cause oesophageal irritation if it remains in prolonged contact with the oesophageal lining. The longer upright window provides a greater margin of safety given the single large dose. This sixty-minute requirement applies from the moment the tablet is swallowed and must be observed precisely.
If you remember within seven days of your usual monthly dosing date, take the missed tablet on the morning you remember, following the usual fasting and upright posture instructions. Then resume your normal monthly date from the following month. If more than seven days have passed since your scheduled date, skip the missed dose entirely and take your next tablet on your usual monthly date in the following month. Never take two ibandronate tablets within the same calendar month. If you are unsure which option applies, contact your pharmacist before taking the missed dose.
Switching from alendronate to ibandronate is a clinical decision that requires prescriber assessment. Both are nitrogen-containing bisphosphonates and have overlapping but not identical licensed indications and tolerability profiles. If you have stopped alendronate due to side effects – particularly gastrointestinal – your prescriber will assess whether ibandronate is an appropriate alternative, taking into account the nature of the adverse effect, your renal function, your bone density history, and the reason the switch is being considered. Do not switch between bisphosphonates without first consulting a prescriber.
Ibandronic acid 150mg is contraindicated in patients with severe renal impairment, defined as creatinine clearance below 30ml per minute. Patients with mild to moderate renal impairment can generally use ibandronate, but renal function should be taken into account during the prescribing consultation. Unlike sodium clodronate, which carries a specific and prominent renal safety concern in combination with NSAIDs, ibandronate does not carry the same labelled drug interaction with anti-inflammatory medicines regarding the kidneys. However, any patient with known renal impairment should disclose this during their consultation so that it can be properly assessed.
Ibandronate does not produce any day-to-day perceptible effect that indicates it is working. Its impact on bone occurs invisibly at the cellular and structural level over months and years of consistent treatment. The standard clinical measure of response is a follow-up DEXA bone density scan, typically performed after two to three years of treatment, which can show whether bone mineral density has increased or stabilised compared to the baseline measurement. Your prescriber will advise on whether and when a follow-up scan is recommended in your individual circumstances. Absence of new fractures during treatment is also a meaningful, if indirect, indicator.
Ibandronate and hormone replacement therapy (HRT) can be used together and are not contraindicated in combination. Both treatments address the bone loss consequences of oestrogen decline following the menopause but through entirely different mechanisms – one pharmacological at the bone surface, the other hormonal. The decision to use both together is a clinical one that involves assessing the individual patient's fracture risk, menopausal symptoms, and medical history. Always ensure your prescriber has a complete picture of all treatments you are using, including HRT in all its forms – patches, tablets, gels, or implants.
Jaw pain, tooth loosening, or numbness in the jaw during treatment should be reported to both your prescriber and your dentist promptly. These may be early signs of osteonecrosis of the jaw, a rare but serious adverse effect associated with bisphosphonate therapy. Separately, new pain that develops gradually in the thigh, hip, or groin – particularly if it is dull and persistent – should be reported to your prescriber without delay, as this may indicate an atypical femoral fracture. Neither symptom should be left until your next scheduled review. Early reporting allows for prompt clinical assessment and, where necessary, imaging.
Yes, in terms of clinical effect. Bonviva is the branded originator product; generic ibandronic acid 150mg tablets contain the same active ingredient at the same dose and are required to demonstrate bioequivalence to Bonviva before they can be licensed for sale in the UK. Bioequivalent means they deliver the same amount of active ingredient into the bloodstream in the same timeframe. Your pharmacy may dispense either the branded or generic version depending on availability and formulary. If you have any concerns about receiving a generic in place of Bonviva, your pharmacist can explain the regulatory basis for the equivalence.
How it works
Complete our online
clinical consultation
clinical consultation
Answer a few questions on your health and your fitness goals.
Clinical
assessment
assessment
Our clinicians will review your clinical questionnaire to make sure treatment is right for you.

Welcome
aboard!
aboard!
Once approved, you will access our wealth of experience and resources curated by our team and begin your clinical journey.
Treatment options
Osteoporosis Treatment Medication
Actonel (Risedronate Sodium) is an osteo ...

Osteoporosis Treatment Medication
Actonel (Risedronate Sodium) is an osteo ...

Alendronic tablets belong to a group of non-hormonal medicines called bisph ...
Alendronic tablets belong to a group of non-hormonal medicines called bisph ...
Alendronic Acid Sugar Free Oral Solution belong to a group of non-hormonal ...

Each capsule of Bonefos Sodium Clodronate contains a disodium clodronate te ...
Need Help?

Do you have a question about weight loss treatment?
Start your weight loss journey heading in the right direction. Our team are here to help. Whether you’re unsure about which medicine is right for you or need help navigating the world of weight loss drugs, our team are on hand to help you make the right decision. We can put you in touch with one of our experienced weight loss clinicians so you can be sure you’re making the best decision with the most accurate information.
To get in touch, contact our Customer Service team on 0800 978 8956 or email headoffice@pharmacyplanet.com.
Meet the team







Review By
GURDEV SEHMI
Last Updated On : Mar 13 2026
BSc Pharm, MRPharmS, Independent Prescriber, Superintendent Pharmacist, Clinical Lead
GPhC Number: 2050925
Authored By
GURDEV SEHMI
Last Reviewed On : Mar 23 2026
BSc Pharm, MRPharmS, Independent Prescriber, Superintendent Pharmacist, Clinical Lead
GPhC Number: 2050925
Get a free consultation
Speak with one of our clinicians and get personalised advice.
You’re almost there!
It is the prescribers duty to ensure that the medicine is being used safely and appropriately. please answer a few questions about yourself to help us process your request.
- Manesha
Customer Service Team
Confidentiality & Authenticity Assured
- Fully Regulated UK Pharmacy
- Authentic UK sourced medicines only.
- Trading for more than 10 years.
- Information Governance lead ensures all data is confidential
Need Help With Your Questionnaire?
Our customer service team is on hand Monday-Friday to help you with your queries.
Please call us on 08009788956 or
email us at: headoffice@pharmacyplanet.com


